Aaaarrgghhh... lagu ni pasal aku 15 - 20 tahun dulu.
Sori ek. Saja nak kongsi.
Kepada Bro Awie & Wings, kalau korang baca blog aku ni..
...jom la kita ubah cara hidup kita.
Si manis di belakang Kowloon rupanya sang khunsa...ahha
Ada jua wajah yg pernah ku lihat di akhbar...auw
Jam 11.30 masih ada tawar menawar (15 ringgit...oh yeah...12 boleh?)
Malam semakin dingin Jalan Chow Kit tetap bahang...uhuk uhuk (oi sakit ker?)
Aku yg lahir di sini rasa macam pendatang haram...haram...(bisa diatur pak)
Yang didusta di kampung berlindung di bukit bintang
Yangg telah pudar usia berlindung di lorong hitam
Hidupnya tersisih sampah masyarakat!...(kesian)
Kota ini penuh dengan projek gajah putih...arghhh
Sungguh indahnya malam tapi aku masih gusar...gusar gusar
Memiikirkan masa depan apa yg harus ku lakukan...oh ma
Kelab malam putar alam ada orang tua menari
Ronggeng frustassi anak bini sedang menanti
Di Sebuah lorong sunyi
Ada tukaran wang dan barang
Di menara tinggi
Ada fitnah sedang berlawan
Gusar menambah lagi
Membuat aku mahu menjerit...jerit
Marah pada siapa marahkan pada blues
Lagu blues tengah malam
Malam malam minggu Yeahh yeahh
Ahh ahh ahaahhh yahuu yahuu yahuuu
yeah yeeehaaaaaa yabedabedu
Wednesday, January 14, 2009

Thursday, January 08, 2009
Kelebihan Jalan Kaki
 Gash kat Kemboja
Sudikah aku kabarkan kepada kalian akan kaum-kaum yang mana mereka itu adalah bukan para anbiyaa` dan bukan pula para syuhadaa`, (walhal) pada hari qiyaamat (nanti) para anbiyaa` dan para syuhadaa` merasa ghibtoh (iri hati) terhadap mereka itu lantaran manaazil (status- status) mereka (begitu dekat) dengan Allah, di atas minbar-minbar daripada nuur mereka dikenali.
Lalu mereka (para Sahabat r.ahum) Bertanya : siapakah mereka itu wahai Rasulullah Shallallaahu 'alayhi wa sallaam? Baginda menjawab (mafhuumnya) : al-ladziina yuhabbibuuna `ibaadaloohi ilAllahi, wa yuhabbibuunAllaha ilaa `ibaadihi, wa yamsyuuna `alal-ardhi nushan; artinya: (yaitu) orang-orang yang menjadikan para hamba Allah dicintai oleh Allah SWT , dan menjadikan Allah SWT dicintai oleh para hambanya, dan mereka itu berjalan kaki di atas (permukaan) bumi dalam hal keadaan memberikan nasihat.
Maka aku berkata : ini menjadikan Allah SWT dicintai oleh para hambanya, maka bagaimanakah mereka menjadikan para hamba Allah SWT dicintai oleh Allah SWT ? Jawab baginda Rasulullah Shallallaahu 'alayhi wa sallaam (mafhuumnya) : mereka itu menyuruh para hamba Allah dengan apa yang Allah SWT suka dan mereka itu mencegah para hamba Allah SWT daripada apa yang Allah SWT benci, maka apabila para hamba Allah SWT itu mentho'ati mereka lalu Allah `azza wa jalla menyintai mereka itu (yakni para hamba Allah itu).
Hayaatush-Shohaabah, juzu` 3, halaman 288 dan 289.
Risalah Fikir (229)
Wednesday, January 07, 2009
Hadeeth About Women Uncovering Their Faces

Artikel ni aku cilok dari sini http://islam-is-beautiful.blogspot.com/
yang terlebih dulu telah menciloknya dari http://islamqa.com/en/cat/56
Baik punya cilok!
*************************************************************************************
Question
How sound is that hadeeth in which the Prophet (peace and blessings of Allaah be upon him) is reported to have said, “When a woman reaches the ages of adolescence, nothing should be seen of her except her face and hands”? How should the Muslim woman dress, based on this? What if extreme hijab will cause problems for a woman in the society in which she lives?.
Answer
Praise be to Allaah.
The hadeeth mentioned in the question was narrated by Abu Dawood (4104) from al-Waleed from Sa’eed ibn Basheer from Qataadah from Khaalid ibn Durayk from ‘Aa’ishah (may Allaah be pleased with her), that Asma’ bint Abi Bakr entered upon the Messenger of Allaah (peace and blessings of Allaah be upon him) wearing a thin dress. The Messenger of Allaah (peace and blessings of Allaah be upon him) turned away from her and said, “O Asma’, when a woman reaches the age of puberty, nothing should be seen of her except this and this” – and he pointed to his face and hands.
Abu Dawood said: This is mursal; Khaalid ibn Durayk did not meet ‘Aa’ishah (may Allaah be pleased with her).
This hadeeth is da’eef (weak) and is not fit to be used as evidence. The reasons why it is da’eef are as follows:
1 – Its isnaad is interrupted, as was stated by Imam Abu Dawood (may Allaah have mercy on him) when he said, “This is mursal; Khaalid ibn Durayk did not meet ‘Aa’ishah.”
2 – Its isnaad includes Sa’eed ibn Basheer al-Azdi (or it was said al-Basri) Abu ‘Abd al-Rahmaan. Some scholars of hadeeth regarded him as thiqah (trustworthy), but Ahmad, Ibn Ma’een, Ibn al-Madeeni, al-Nasaa’i, al-Haakim and Abu Dawood regarded him as da’eef. (weak).
Muhammad ibn ‘Abd-Allaah ibn Numayr said of him: His hadeeth is to be rejected and he does not amount to anything, and he is not strong in hadeeth. He narrated munkar reports from Qataadah.
Ibn Hibbaan said of him: He has a bad memory and makes grievous mistakes.
Al-Haafiz ibn Hajar said of him: (he is) da’eef.
3 – Its isnaad includes Qataadah who is mudallis (i.e., gives false impressions concerning the narration of the hadeeth) and did not clearly state that he heard the hadeeth from another. It also includes al-Waleed ibn Muslim of whom al-Haafiz said: (he is) trustworthy but he was also mudallis and did not clearly state that he heard the hadeeth from another.
These are the faults in the hadeeth because of which the hadeeth was judged to be da’eef (weak). See Fataawa al-Lajnah al-Daa’imah, Majallat al-Buhooth, 21/68.
Even if we assume that the hadeeth is saheeh or is strengthened by corroborating reports, the scholars have also noted that this incident occurred before hijab was enjoined. Ibn Qudaamah said: “With regard to the hadeeth of Asma’, it is to be understood as having occurred before the verse of hijab was revealed.”
Shaykh Muhammad ibn ‘Uthaymeen (may Allaah have mercy on him) said: “Even if we assume it is saheeh, it is to be interpreted as referring to the time before hijab was revealed.” See ‘Awdat al-Hijaab, 3/336.
If we study the text of the hadeeth , we will find that it is extremely unlikely, because Asma’ (may Allaah be pleased with her) was very pious and modest, so she would not have worn these thin clothes and appeared in them in front of the Messenger (peace and blessings of Allaah be upon him).
The correct view on this matter is that it is obligatory for women to cover their entire bodies in front of non-mahram men. See question no. 21134.
If hijab is going to lead to problems for a woman in the society in which she lives, then she must be patient and seek reward for the problems she encounters for the sake of adhering to her religion and obeying her Lord. We have a good example in our righteous forebears, may Allaah be pleased with them, because they were persecuted severely for the sake of Allaah, but that did not turn them away from their religion, rather the persecution and torment only increased their adherence to their religion. Perhaps the days we are living through are the days of patience of which the Prophet (peace and blessings of Allaah be upon him) told us when he said: “There will come a time of patience when the one who adheres steadfastly to his religion will be like one who holds a burning coal.” Narrated by al-Tirmidhi, 2260; classed as saheeh by al-Albaani in al-Silsilah al-Saheehah, 957.
Al-Qaari said: The apparent meaning of this hadeeth is that just as it is impossible to hold on to a burning coal except with intense patience and great difficulty, at that time no one will be able to adhere to his religion and the light of faith except with great patience.
From Tuhfat al-Ahwadhi.
Al-Mannaawi said in Fayd al-Qadeer:
The one who is patient in adhering to the rulings of the Qur’aan and Sunnah is likened, in the difficulties that he encounters from the followers of innovation and misguidance, to one who takes hold of fire; it may be even more difficult than that. This is one of the miracles of the Prophet (peace and blessings of Allaah be upon him): he spoke of the unseen and it came to pass.
We ask Allaah to make us steadfast in adhering to His religion until we meet Him.
And Allaah knows best.
Islam Q&A
Monday, January 05, 2009
Derma Buah Pinggang

Jika tuan/puan, saudara/saudari mempunyai darah A+ dan ingin menderma buah pinggang kepada anak saya Muhammad Ammar, untuk dapatkan borang sila layari;
http://www.agiftoflife.gov.my/organdonor.html
* Sertakan sekali satu surat yang mengatakan anda ingin agar Muhammad Ammar bin Mohd Azhar, no pesakit 244714 yang berdaftar dengan Hospital Selayang menjadi pilihan pertama sebagai penerima buah pinggang anda.
Kisah Muhammad Ammar baca di sini;
http://azharjaafar313.blogspot.com/2008/11/aku-sekarang-kat-hospital.html
http://azharjaafar313.blogspot.com/2008/12/hospital-selayang.html
http://azharjaafar313.blogspot.com/2008/12/capd.html
Perbincangan ulama mengenai derma buah pinggang;
http://www.zaharuddin.net/content/view/183/90/
http://saifulislam.com/?p=518
http://baheis.islam.gov.my/web/musykil_new.nsf/92be69fae3f225c0482567f1005a8e7b/326e4a566d01d58b4825739000613978?OpenDocument
http://drmaza.com/home/?p=76
http://www.bicaramuslim.com/bicara7/viewtopic.php?f=21&t=6206&start=0&st=0&sk=t&sd=a
Mudah-mudahan bantuan anda diterima Allah dan Muhammad Ammar dapat menggunakan seluruh hidupnya untuk memperjuangkan agama Allah. Amin.
Pakaian Dan Kerja

Lain macam je tajuk entry kali ni bang. Eyelah..
Disebalik setiap pakaian, mesti la ada kerja. Orang yang pakai baju polis, mestilah kerja polis. Tak kan merompak pulak. Disebalik baju doktor, tentu ada kerja. Kerja doktor. Kalau nampak hensem semacam je dengan kemeja dan slack, agak-agak ni mesti kerja opis. Tak pun salesman. Begitu jugak dengan student, nurse, pekerja Alam Flora...
Aik? Student pun ada pakaian. Ada.. fesyen student la. Tak kan pakai ihram masuk kelas..
Kalau diorang-diorang ni bergaya dengan pakaian masing-masing tapi tak buat kerja, amacam? Mungkin;
- dapat surat warning
- kena pulau
- kena kutuk
- makan gaji buta (memang pun)
- kena berenti kerja
- kena pukul
- tahap kronik; kena bunuh!
- dll
Kalau orang tanya kita; "Kau orang Islam ke?"
Cepat-cepat kita jawab; "Ya."
"Apa kerja orang Islam?"
"Apa ye? Solat, puasa, zakat, haji dan lain-lain ibadat la."
"Itu pakaian orang Islam, tapi kerja, kerja.."
"Ada kerja lain ke?"
Jadi bila tak buat kerja, dapatlah 8 perkara di atas. Dah la tak buat kerja, tak tahu pulak tu kerja. Yang dah tahu malas pulak nak belajar kerja atau buat-buat tak tahu kerja tu...
Gaji nak, kerja tak nak..
Lepas tu memekik.. melalak... demonstrasi.. ngata orang!
Sendri mau ingat.
Friday, January 02, 2009
Ijtimak Malaysia 2009 - persiapan

Pada Rabu 31/12/2009 yang lepas, Allah SWT beri peluang aku hadir ke mesyuarat mingguan Kuala Lumpur di Masjid Sri Petaling. Mesyuarat start pukul 6.15 petang. Asbab keluar lambat dari Kepong, aku bersama 3 lagi kengkawan terperangkap dalam jem. Maklumlah kat KL ni lepas jam 5 petang jalan mula sesak. Orang berpusu-pusu balik dari kerja. Malam tahun baru pulak tu!
Cerita pasal tahun baru (masehi), tengahari tadi (Rabu 31/12/2009) sorang member kamcing lama telefon. Dia bertanya hal Ammar. Dalam pada tu dia tanya aku, malam ni tak turun KL ke sambut tahun baru? Soalan tu menyebabkan kami sama-sama gelak besar! Teringat dulu-dulu zaman bujang (belum dapat hidayat), bila malam tahun baru... Alamatnya sampai ke pagi baru balik. Member aku kata, dulu bila aku ajak dia kepada benda-benda tak elok, cepat je dia ikut. Sekarang bila aku ajak dia ke benda-benda baik, tak nak pulak dia ikut. Mmm... tahu tak pe...
Balik pada hal mesyuarat KL. Sampai dah dekat Maghrib. Sempat menge'teh' dulu. Alamatnya lepas Maghrib la baru dapat duduk dalam mesyuarat. Perbincangan banyak berkisar hal ijtimak Malaysia yang dijangka dibuat pada bulan Julai 2009. Macamanapun tarikh sebenar dan tempat nak dibuat ijtimak belum diputuskan lagi. Fuh.. bahang ijtimak memang terasa bila duduk dalam mesyuarat ni. Banyak persediaan nak dibuat.
Antara targhib yang dibuat; 'Kejayaan ijtimak adalah bergantung kepada usaha yang dibuat sebelum ijtimak. Usaha ijtimak telah bermula sejak 16/10/2008 lagi iaitu pada hari elders putuskan untuk mengadakan ijtimak. Oleh itu jemaah hendaklah dikeluarkan sebanyak-banyak nya sebelum ijtimak. Jemaah yang keluar sebelum ijtimak adalah ruh kepada ijtimak. Manakala jemaah yang keluar selepas ijtimak adalah sebagai perhiasan ijtimak.'
Untuk Kuala Lumpur (termasuk Selangor), jemaah 2 bulan khas untuk usuli kawasan-kawasan dibentuk. Jemaah yang keluar dari bulan November dan Disember dah tangguh. Jadi ditashkil untuk jemaah baru untuk bulan Januari dan Februari yang akan diberi bayan hidayat pada 01/01/2009. MasyaAllah! Tashkil 'cash' tuh.. Malam ni tashkil, esok nak keluar. Alhamdulillah kira-kira 10 orang sedia keluar tunai. Hebat Allah. Dalam zaman manusia sebuk mencari dunia, masih ada manusia yang sedia sambut takaza untuk keluar tunai macam tu.
Lepas tu ditashkil untuk jemaah 4 bulan jalan kaki yang dijangka dikeluarkan pada 15/02/2009. Beberapa orang dah bagi nama. Mereka terus dikumpul dalam bilik syura dan terus ditafakut oleh syura Malaysia. Masih tak cukup orang. Targhib lagi.. tashkil lagi.. Jantung aku berdebar-debar. Keinginan nak keluar ada, tapi banyak sangat pikir. Macam-macam pikir. Yang aku tahu kebanyakannya adalah ilham syaitan untuk menakut-nakutkan aku dari keluar di jalan Allah.
Akhirnya dengan izin Allah, aku bangun bagi nama. Tiada daya dan upaya melainkan dengan izin Allah. Fuhhh.. satu kepuasan dan ketenangan bila dapat bangun dan bagi nama. Alhamdulillah tafakut dah lulus dan jemaah aku lebih kurang 10 orang dapat dibentuk. Semua dalam jemaah ni adalah orang lama kecuali aku, orang yang PALING tak lama. Semoga Allah terima kita semua dan keluarga dan umat ni untuk jadi pembantu agama Allah. Kengkawan semua, tolong la doa untuk aku yang lemah ni.
Saturday, December 27, 2008
CAPD
Inilah jenis rawatan buah pinggang yang sedang dijalani Ammar sekarang.


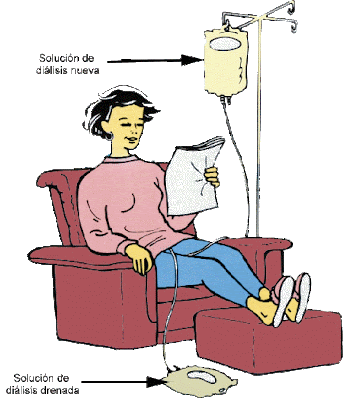
Tiada yang berkuasa melainkan Allah. Yang mencipta, memelihara dan mentadbir sekalian makhluk. DitanganNya lah penguasaan langit dan bumi, dunia dan akhirat.
InsyaAllah Ammar boleh balik hari ni atau Selasa depan. Doa untuk Ammar dan umat.
Introduction
Current treatment options for patients with severe chronic kidney failure are dialysis and kidney transplantation. Dialysis is a treatment that removes substances such as water, salts, and waste products (from the body’s normal metabolism), which build up in patients with failing kidneys. There are two forms of dialysis. One is called hemodialysis (HD), where the blood is cleaned outside the body and then returned to the body. This treatment, done in a hospital, or a dialysis clinic, is normally done 3 times a week, where each session takes about 4 hours. In HD, a machine and a filter are required, as well as a system to get the blood out of the body, as well as returning the cleaned blood to the patient. In most patients, this so called access to the blood, is done by inserting two needles into blood vessels on the forearm. A few centers around the world can train patients for self- HD. In regard to transplantation, the new kidney can come from either a deceased person or a living donor.
Fun fact: in 1972, a law was passed that medical care had to cover dialysis and kidney transplants.
What is peritoneal dialysis (PD) and how does it work?
The other form of dialysis is called peritoneal dialysis (PD). More than 150,000 patients are currently receiving this lifesaving treatment around the world.
In PD, a dialysis fluid is entered into the patient’s abdominal (= peritoneal) cavity (the “belly”), which is covered by a thin membrane, containing many small blood vessels. This membrane, called the peritoneum, is like a big bag that keeps the stomach, intestines, liver, and other organs in place. The dialysis fluid will make water, salts, and the waste products move from the blood into the fluid (also called solution). This process is called dialysis, and means that the peritoneum works as a dialysis filter. As the fluid gets saturated after a while, the solution must be exchanged regularly (see below).
The solutions
The fluids contain either sugar (glucose), amino acids, which are building blocks for proteins, or a compound called icodextrin, to remove the water. The sugar solution is the one most commonly used. The glucose “strength” (1.5%, 2.5% or 4.25%) of the solution determines how much water is removed from the blood; the higher the concentration, the greater the water removal. The amino acid solution is used to improve a patient’s nutritional condition (as the amino acids are taken up by the body, i.e. they move from the solution to the blood), and/ or to reduce the uptake of glucose from the solution. The benefits of the icodextrin fluid is that it removes more water than the glucose solution for longer exchange intervals, and that it is glucose- free, which is advantageous both for the peritoneum and the body as a whole.
There are two types of glucose solutions. The main difference is the pH, and the type of substance added to reduce the acidity of the blood, which is common in patients with kidney disease.
How can the solution be exchanged?
A small plastic tube, called a catheter, which has been placed through the abdominal wall in a small operation done before starting PD, is used to let the fluid go in to, and out from, the abdomen. The place where the catheter comes out is called the “exit site”. The catheter can normally be used for many years if so needed. In most cases two liters of fluid is entered each time, and is exchanged 4 times per day. In the beginning the patient may feel some discomfort when the solution goes in, but this normally disappears after a while. The bags are delivered to the patient’s home at regular intervals.
Preparation for the exchange
The recommended procedure varies somewhat between centers, but in most cases the patient wears a disposable surgical mask, and scrubs the hands for 3 minutes using soap and water. The solution should be warmed to body temperature before use, for example by using a heating pad or a heating plate. Many centers will provide the patients with an appropriate heating device to be used at home.
Two methods for the solution exchange/ types of PD
There are two types of PD: CAPD and APD. The difference is that in CAPD the exchanges are done manually, and in APD automatically by a small machine.
CAPD means: Continuous Ambulatory Peritoneal Dialysis
C- continuous: dialysis solution is always inside the “belly” cleansing the blood in a continuous manner.
A- ambulatory: ambulatory means that between exchanges, one can move about freely and continue normal activities like going for a drive, walking, golfing, studying or sleeping. In CAPD the solution exchanges are done manually at home, normally with 4 exchanges daily, seven days a week, by the patient him/herself.
P- peritoneal: this type of dialysis makes use of the peritoneal membrane that covers the peritoneal cavity in order to cleanse the blood of waste products and water.
D- dialysis: dialysis is the process of removing all wastes and excess water from the blood, in PD using the peritoneal membrane as a filter.
Steps in CAPD are
Step 1) Attach the new bag
Step 2) Drain: this means letting the solution go from the peritoneal cavity (by gravity) to the so-called drain bag, which takes 15-20 minutes
Step 3) Flush: this is when the system is ‘flushed’ with unused solution for approximately 10 seconds. This ensures your system is made clear of bacteria that may have entered the system when the new bag was connected
Step 4) Fill: this means filling the new solution into the peritoneal cavity. This normally takes less than 10 minutes
Step 5) Dwell time: this is when the dialysis solution is inside the peritoneal cavity
APD means: Automated Peritoneal Dialysis
A- Automated: automated means that the fluid exchanges are done automatically by a machine. In APD, the treatment is done at home at night while sleeping. Most patients are prescribed a continuous (see above) treatment, but in some cases it may be possible to have no dialysis during the day, which means no fluid in “the belly” at daytime.
The steps in APD are
Step 1) Start the machine
Step 2) Connect the new bags
Step 3) Connect to machine
Step 4) The fluid exchanges are done by the machine during the night
Step 5) Disconnect from the machine
Travel
Travel is possible with both CAPD and APD, as the bags can be delivered to the visiting areas. In APD the small size of the machine (such as HomeChoice, manufactured by Baxter) makes it easy to travel despite the PD treatment.
Disposing of the drained fluid
Patients can empty the bags containing the drained fluid into the toilet.
Advantages and disadvantages of peritoneal dialysis
Advantages
A. Compared to HD
* Treatment at home, which means no travel to a HD unit 3 times a week.
* Self control of the therapy
* No needles required
* Facilitates employment
* Easy travel
* Better preservation of the remaining kidney function, which is very important because it helps removing the water and the waste products. This reduces the need for a high dose of dialysis, and also improves patients’ survival and their quality of life.
* Lower doses of medication needed to treat anemia
* Lower risk for hepatitis B and C (liver infections caused by virus)
* Better results after kidney transplantation
* The removal of water is more gentle
B. General
* Easy to learn (3-5 days)
* High level of patient satisfaction and well-being
Disadvantages
* Peritonitis is an infection in the peritoneal cavity. This is in most cases caused by bacteria entering the fluid pass at a solution exchange procedure. The risk for such an infection is nowadays low (on average one episode every 3-5 years) due to improvements in the design of the products used. Also, following the instructions about how to exchange the fluids will further reduce the risk. Usually, a patient with peritonitis has fever, abdominal pain and a cloudy appearance of drained dialysis fluid. Peritonitis is treated, and normally cured, by using antibiotics. Sometimes a change of the catheter or a change of dialysis therapy (temporarily or permanently) may be necessary.
* Exit site infection is an infection of the “exit site” (=where the catheter comes out through the skin) and normally caused by bacteria. Common signs of such an infection are redness and secretion at the exit site. Antibiotics are given to cure the infection. There are also simple ways to prevent the occurrence of exit site infection, such as changing clothes daily, and always wash and dry hands before touching the catheter and exit site.
* Membrane function With time on PD, the peritoneal membrane may change its capability to remove enough water and wastes, which can require a need to change the prescription. In some cases, mainly after many years of PD (more than 5 years), this may not be sufficient, and a change to HD may be needed.
Summary
PD is a home- based therapy and widely used around the world. In general, it is easy, convenient, safe and effective for most patients with failing kidneys.


Tiada yang berkuasa melainkan Allah. Yang mencipta, memelihara dan mentadbir sekalian makhluk. DitanganNya lah penguasaan langit dan bumi, dunia dan akhirat.
InsyaAllah Ammar boleh balik hari ni atau Selasa depan. Doa untuk Ammar dan umat.
Introduction
Current treatment options for patients with severe chronic kidney failure are dialysis and kidney transplantation. Dialysis is a treatment that removes substances such as water, salts, and waste products (from the body’s normal metabolism), which build up in patients with failing kidneys. There are two forms of dialysis. One is called hemodialysis (HD), where the blood is cleaned outside the body and then returned to the body. This treatment, done in a hospital, or a dialysis clinic, is normally done 3 times a week, where each session takes about 4 hours. In HD, a machine and a filter are required, as well as a system to get the blood out of the body, as well as returning the cleaned blood to the patient. In most patients, this so called access to the blood, is done by inserting two needles into blood vessels on the forearm. A few centers around the world can train patients for self- HD. In regard to transplantation, the new kidney can come from either a deceased person or a living donor.
Fun fact: in 1972, a law was passed that medical care had to cover dialysis and kidney transplants.
What is peritoneal dialysis (PD) and how does it work?
The other form of dialysis is called peritoneal dialysis (PD). More than 150,000 patients are currently receiving this lifesaving treatment around the world.
In PD, a dialysis fluid is entered into the patient’s abdominal (= peritoneal) cavity (the “belly”), which is covered by a thin membrane, containing many small blood vessels. This membrane, called the peritoneum, is like a big bag that keeps the stomach, intestines, liver, and other organs in place. The dialysis fluid will make water, salts, and the waste products move from the blood into the fluid (also called solution). This process is called dialysis, and means that the peritoneum works as a dialysis filter. As the fluid gets saturated after a while, the solution must be exchanged regularly (see below).
The solutions
The fluids contain either sugar (glucose), amino acids, which are building blocks for proteins, or a compound called icodextrin, to remove the water. The sugar solution is the one most commonly used. The glucose “strength” (1.5%, 2.5% or 4.25%) of the solution determines how much water is removed from the blood; the higher the concentration, the greater the water removal. The amino acid solution is used to improve a patient’s nutritional condition (as the amino acids are taken up by the body, i.e. they move from the solution to the blood), and/ or to reduce the uptake of glucose from the solution. The benefits of the icodextrin fluid is that it removes more water than the glucose solution for longer exchange intervals, and that it is glucose- free, which is advantageous both for the peritoneum and the body as a whole.
There are two types of glucose solutions. The main difference is the pH, and the type of substance added to reduce the acidity of the blood, which is common in patients with kidney disease.
How can the solution be exchanged?
A small plastic tube, called a catheter, which has been placed through the abdominal wall in a small operation done before starting PD, is used to let the fluid go in to, and out from, the abdomen. The place where the catheter comes out is called the “exit site”. The catheter can normally be used for many years if so needed. In most cases two liters of fluid is entered each time, and is exchanged 4 times per day. In the beginning the patient may feel some discomfort when the solution goes in, but this normally disappears after a while. The bags are delivered to the patient’s home at regular intervals.
Preparation for the exchange
The recommended procedure varies somewhat between centers, but in most cases the patient wears a disposable surgical mask, and scrubs the hands for 3 minutes using soap and water. The solution should be warmed to body temperature before use, for example by using a heating pad or a heating plate. Many centers will provide the patients with an appropriate heating device to be used at home.
Two methods for the solution exchange/ types of PD
There are two types of PD: CAPD and APD. The difference is that in CAPD the exchanges are done manually, and in APD automatically by a small machine.
CAPD means: Continuous Ambulatory Peritoneal Dialysis
C- continuous: dialysis solution is always inside the “belly” cleansing the blood in a continuous manner.
A- ambulatory: ambulatory means that between exchanges, one can move about freely and continue normal activities like going for a drive, walking, golfing, studying or sleeping. In CAPD the solution exchanges are done manually at home, normally with 4 exchanges daily, seven days a week, by the patient him/herself.
P- peritoneal: this type of dialysis makes use of the peritoneal membrane that covers the peritoneal cavity in order to cleanse the blood of waste products and water.
D- dialysis: dialysis is the process of removing all wastes and excess water from the blood, in PD using the peritoneal membrane as a filter.
Steps in CAPD are
Step 1) Attach the new bag
Step 2) Drain: this means letting the solution go from the peritoneal cavity (by gravity) to the so-called drain bag, which takes 15-20 minutes
Step 3) Flush: this is when the system is ‘flushed’ with unused solution for approximately 10 seconds. This ensures your system is made clear of bacteria that may have entered the system when the new bag was connected
Step 4) Fill: this means filling the new solution into the peritoneal cavity. This normally takes less than 10 minutes
Step 5) Dwell time: this is when the dialysis solution is inside the peritoneal cavity
APD means: Automated Peritoneal Dialysis
A- Automated: automated means that the fluid exchanges are done automatically by a machine. In APD, the treatment is done at home at night while sleeping. Most patients are prescribed a continuous (see above) treatment, but in some cases it may be possible to have no dialysis during the day, which means no fluid in “the belly” at daytime.
The steps in APD are
Step 1) Start the machine
Step 2) Connect the new bags
Step 3) Connect to machine
Step 4) The fluid exchanges are done by the machine during the night
Step 5) Disconnect from the machine
Travel
Travel is possible with both CAPD and APD, as the bags can be delivered to the visiting areas. In APD the small size of the machine (such as HomeChoice, manufactured by Baxter) makes it easy to travel despite the PD treatment.
Disposing of the drained fluid
Patients can empty the bags containing the drained fluid into the toilet.
Advantages and disadvantages of peritoneal dialysis
Advantages
A. Compared to HD
* Treatment at home, which means no travel to a HD unit 3 times a week.
* Self control of the therapy
* No needles required
* Facilitates employment
* Easy travel
* Better preservation of the remaining kidney function, which is very important because it helps removing the water and the waste products. This reduces the need for a high dose of dialysis, and also improves patients’ survival and their quality of life.
* Lower doses of medication needed to treat anemia
* Lower risk for hepatitis B and C (liver infections caused by virus)
* Better results after kidney transplantation
* The removal of water is more gentle
B. General
* Easy to learn (3-5 days)
* High level of patient satisfaction and well-being
Disadvantages
* Peritonitis is an infection in the peritoneal cavity. This is in most cases caused by bacteria entering the fluid pass at a solution exchange procedure. The risk for such an infection is nowadays low (on average one episode every 3-5 years) due to improvements in the design of the products used. Also, following the instructions about how to exchange the fluids will further reduce the risk. Usually, a patient with peritonitis has fever, abdominal pain and a cloudy appearance of drained dialysis fluid. Peritonitis is treated, and normally cured, by using antibiotics. Sometimes a change of the catheter or a change of dialysis therapy (temporarily or permanently) may be necessary.
* Exit site infection is an infection of the “exit site” (=where the catheter comes out through the skin) and normally caused by bacteria. Common signs of such an infection are redness and secretion at the exit site. Antibiotics are given to cure the infection. There are also simple ways to prevent the occurrence of exit site infection, such as changing clothes daily, and always wash and dry hands before touching the catheter and exit site.
* Membrane function With time on PD, the peritoneal membrane may change its capability to remove enough water and wastes, which can require a need to change the prescription. In some cases, mainly after many years of PD (more than 5 years), this may not be sufficient, and a change to HD may be needed.
Summary
PD is a home- based therapy and widely used around the world. In general, it is easy, convenient, safe and effective for most patients with failing kidneys.
Saturday, December 20, 2008
Depression vs Contentment
Talk by Sheikh Sulaiman Mulla.
Most Islamic scholars and pious Muslims of the early generations of Islam were poor; needless it is to say, then, that they did not have beautiful houses or nice cars. Yet, despite these disadvantages, they led fruitful lives, and they benefited mankind, not by some miracle, but because they used all that they were given, and spent their time in the correct way. Hence they were blessed in their lives, their time, and their talents.
On the contrary, there are many people who have been bestowed with wealth, children, and all forms of blessings, yet these blessings have been the very reason for their misery and ruin.
Most Islamic scholars and pious Muslims of the early generations of Islam were poor; needless it is to say, then, that they did not have beautiful houses or nice cars. Yet, despite these disadvantages, they led fruitful lives, and they benefited mankind, not by some miracle, but because they used all that they were given, and spent their time in the correct way. Hence they were blessed in their lives, their time, and their talents.
On the contrary, there are many people who have been bestowed with wealth, children, and all forms of blessings, yet these blessings have been the very reason for their misery and ruin.
* Part 1/2
* Part 2/2
Friday, December 19, 2008
Hospital Selayang
Firman Allah dalam surah Al Baqarah, mafhumnya;
[155]
Demi sesungguhnya! Kami akan menguji kamu dengan sedikit perasaan takut (kepada musuh) dan (dengan merasai) kelaparan, dan (dengan berlakunya) kekurangan dari harta benda dan jiwa serta hasil tanaman. Dan berilah khabar gembira kepada orang-orang yang sabar:
[156]
(Iaitu) orang-orang yang apabila mereka ditimpa oleh sesuatu kesusahan, mereka berkata: “Sesungguhnya kami adalah kepunyaan Allah dan kepada Allah jualah kami kembali.”
[157]
Mereka itu ialah orang-orang yang dilimpahi dengan berbagai-bagai kebaikan dari Tuhan mereka serta rahmatNya; dan mereka itulah orang-orang yang dapat petunjuk hidayahNya.
Aku & family semenjak Ammar masuk hospital pada 5hb Nov 2008.
 Hari-hari awal Ammar di hospital tak dapat tidur baring sebab susah bernafas bila paru-paru berair.
(kegagalan buah pinggang berfungsi menyebabkan air memenuhi badan, darah tinggi naik dan tekanan jantung jadi lemah. Hebat engkau Ya Allah!)
 Bapak misali (ceh, ceh..)
 Ada aktiviti pulak pada satu hari 22 Nov 2008.
 Hasil karya Ammar.
 Ammar yang ceria selepas melalui proses cuci darah melalui lehernya.
 Majlis taklim (bacaan hadis fadhail) selepas Isya'.
 Amir yang balik cuti pada raya Haji lepas.
 Mu'az tido.
 Mardhiah pun tido.
 Ammar dan rakan-rakan.
Doa untuk Ammar dan umat.
Syukuri lah nikmat iman, Islam dan kesihatan yang Allah bagi kat kita.
*Posting berkaitan.
[155]
Demi sesungguhnya! Kami akan menguji kamu dengan sedikit perasaan takut (kepada musuh) dan (dengan merasai) kelaparan, dan (dengan berlakunya) kekurangan dari harta benda dan jiwa serta hasil tanaman. Dan berilah khabar gembira kepada orang-orang yang sabar:
[156]
(Iaitu) orang-orang yang apabila mereka ditimpa oleh sesuatu kesusahan, mereka berkata: “Sesungguhnya kami adalah kepunyaan Allah dan kepada Allah jualah kami kembali.”
[157]
Mereka itu ialah orang-orang yang dilimpahi dengan berbagai-bagai kebaikan dari Tuhan mereka serta rahmatNya; dan mereka itulah orang-orang yang dapat petunjuk hidayahNya.
Aku & family semenjak Ammar masuk hospital pada 5hb Nov 2008.
 Hari-hari awal Ammar di hospital tak dapat tidur baring sebab susah bernafas bila paru-paru berair.
(kegagalan buah pinggang berfungsi menyebabkan air memenuhi badan, darah tinggi naik dan tekanan jantung jadi lemah. Hebat engkau Ya Allah!)
 Bapak misali (ceh, ceh..)
 Ada aktiviti pulak pada satu hari 22 Nov 2008.
 Hasil karya Ammar.
 Ammar yang ceria selepas melalui proses cuci darah melalui lehernya.
 Majlis taklim (bacaan hadis fadhail) selepas Isya'.
 Amir yang balik cuti pada raya Haji lepas.
 Mu'az tido.
 Mardhiah pun tido.
 Ammar dan rakan-rakan.
Doa untuk Ammar dan umat.
Syukuri lah nikmat iman, Islam dan kesihatan yang Allah bagi kat kita.
*Posting berkaitan.
Sunday, December 14, 2008
Our Imaan

Its indeed necessary [not optional] for us to think deeply about the exact condition of our Imaan. Now at the present situations, Muslim Ummah are putting hard and soul efforts for developing their careers but are they really giving equal time for thinking about Imaan?
Our Rasool Muhammad [Sallallahu Alayhi Wasallam] passed nights after nights awaking, crying, giving da'wah, fasting during hot summer, performing Salaths at nights, making Du'aa for Ummah and we, the follower of Muhammad [ Sallallahu Alayhi Wasallam] sleeping in Air Conditioning rooms without even neglecting Salath? How can we stand in front of Allah Taa'la in the day of Qiyamah!
Allah Taa'la said in Quran [059:19]
"And be not like those who forgot Allah and He caused them to forget their ownselves. Those are the Fâsiqûn (rebellious, disobedient to Allah)."
One Muslim philosopher [Rohmatullah] used to ask Allah Taa'la like "Ya Allah, eyes are in our control but we can't control our eyes. Hands are in our control but we can't resist hands of doing wrong works. Legs are in our control but we even can't control our legs of going bad places but Imaan is not in our control then how can we guard our Imaan. So Allah, please secure our Imaan with your blessings and mercy."
SubhanAllah!
So my brothers n sisters we need to be very careful to guard our Imaan from all evil works. The most evil crime is forgetting Allah Taa'la. We also need to make du'aa all time so that Allah Taa'la helps us to guard our Imaan with His own rahmat.
Saturday, December 13, 2008
Allah Maha Pencipta
Artikel di bawah diambil dari http://atehfaisal.blogspot.com
****************************************
Syukur...
maha suci Allah, pentadbir seluruh alam dan seisinya. Ilmu Allah amat hebat dan segalanya tidak mustahil terjadi. Inilah bukti kekuasaan Allah SWT untuk hamba-hambanya melihat, dan berfikir tentang kebesaran dan kekuasaan Allah yg tidak terhingga.
Saksikan gambar di bawah. Musytari (Jupiter), Kejora (Venus) dan Bulan kelihatan harmoni dan dekat antara satu sama lain (seolah sedang tersenyum) sedangkan pada hakikat sebenar, 3 makhluk Allah itu adalah berbilion-bilion tahun cahaya jaraknya antara satu sama lain. MasyaAllah...


kejadian Allah yg mengagumkan aku malam ni...
Bulan bersama-sama dengan Mustytari (jupiter) dan Kejora (venus)berhimpun di dalam kawasan yang sama dan membentuk sebuah segitiga! seperti sedang tersenyum.
Bayangkan, walaupun ketiga-tiga objek ini dilihat seolah-olah hampir antara satu sama lain, tetapi dari segi hakikatnya tidak.
Cahaya dari Bulan mengambil masa 1.3 saat untuk sampai ke mata kita. Cahaya dari Kejora (objek sebelah kiri), mengambil masa lebih kurang 8 minit untuk sampai. Manakala Musytari yang dilihat itu ialah keadaannya 48 minit terdahulu!
 conjunction as seen by peoples of East Asia & Oceania.
 conjunction as seen by viewers from Central & West Asia Regions & East part of Europe
 conjunction as seen by viewers from Western Europe.
 conjunction as seen by viewers from South American Regions.
****************************************
Syukur...
maha suci Allah, pentadbir seluruh alam dan seisinya. Ilmu Allah amat hebat dan segalanya tidak mustahil terjadi. Inilah bukti kekuasaan Allah SWT untuk hamba-hambanya melihat, dan berfikir tentang kebesaran dan kekuasaan Allah yg tidak terhingga.
Saksikan gambar di bawah. Musytari (Jupiter), Kejora (Venus) dan Bulan kelihatan harmoni dan dekat antara satu sama lain (seolah sedang tersenyum) sedangkan pada hakikat sebenar, 3 makhluk Allah itu adalah berbilion-bilion tahun cahaya jaraknya antara satu sama lain. MasyaAllah...


kejadian Allah yg mengagumkan aku malam ni...
Bulan bersama-sama dengan Mustytari (jupiter) dan Kejora (venus)berhimpun di dalam kawasan yang sama dan membentuk sebuah segitiga! seperti sedang tersenyum.
Bayangkan, walaupun ketiga-tiga objek ini dilihat seolah-olah hampir antara satu sama lain, tetapi dari segi hakikatnya tidak.
Cahaya dari Bulan mengambil masa 1.3 saat untuk sampai ke mata kita. Cahaya dari Kejora (objek sebelah kiri), mengambil masa lebih kurang 8 minit untuk sampai. Manakala Musytari yang dilihat itu ialah keadaannya 48 minit terdahulu!
1-12-2008 ~ Conjunction Pics Around Globe
 conjunction as seen by peoples of East Asia & Oceania.
 conjunction as seen by viewers from Central & West Asia Regions & East part of Europe
 conjunction as seen by viewers from Western Europe.
 conjunction as seen by viewers from South American Regions.
Subscribe to:
Posts (Atom)
Membetulkan Solat
Nasihat Hazratji Maulana Saad DB Alami Markaz Banglawalee Masjid, Nizammuddin. "Adalah penting untuk kita semua memperbetul...

-
 Peta Perancis ~Apa kena mengena dengan entry aku ni, aku pun tak tahu.. Para Sahabat Keluar ke Jalan Allah Sebanyak 150 jemaah telah dihanta...
-
 The story says that Hajaj bin Yusuf has ordered his army to catch Hazrat Anas رضي الله عنه from Madinah. Once they bring him to Hajaj, he w...